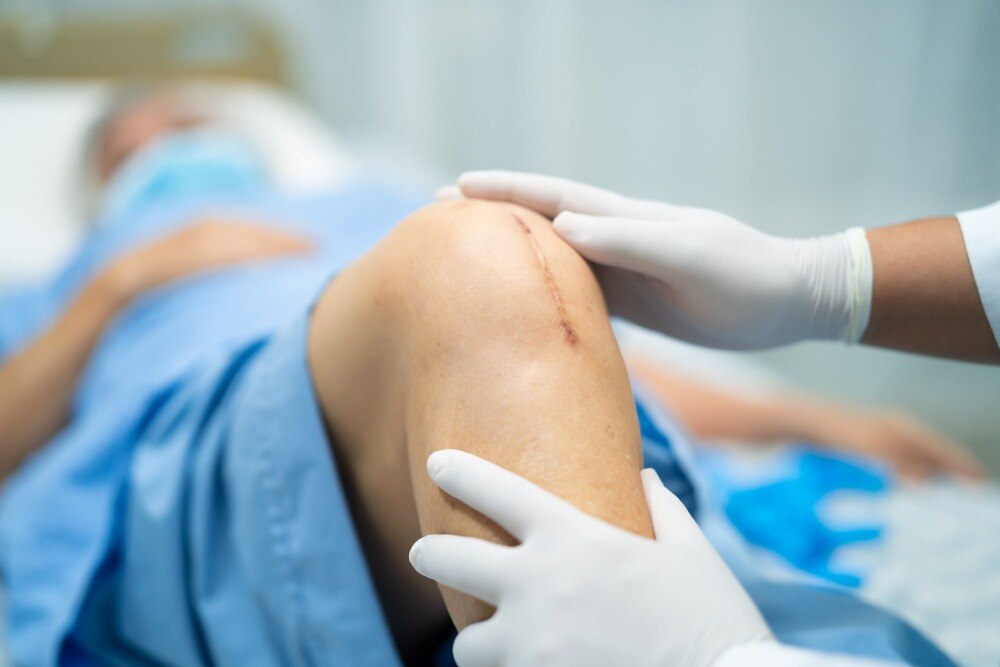
A job that involves standing, walking, stairs, lifting or squatting does not automatically rule out knee replacement, but it does raise practical questions about implant choice, recovery and safe return to work. You will learn which symptoms justify a surgical discussion, how age and job demands affect suitability, and how to plan a return without confusing a healed incision with readiness for a full shift.
Key takeaways
- Consider surgery when pain and lost function persist despite structured nonsurgical treatment.
- Match treatment to arthritis severity, knee damage, job demands and health—not age alone.
- Plan a phased return if your work requires prolonged standing, walking, lifting or kneeling.
- Ask the surgeon about restrictions, rehabilitation milestones and workplace adjustments before surgery.
When should a working adult consider knee replacement?
Discuss knee replacement when knee pain and loss of function continue despite a structured treatment plan. That plan can include physiotherapy, strengthening, weight management when appropriate, medicines, injections and activity modification.
A standing job alone does not indicate surgery; knee replacement for people who work on their feet becomes relevant when the knee prevents safe, reliable work and daily activity.
Signs that deserve a surgical discussion include:
- Pain that builds during a full shift or continues at night
- Difficulty climbing or descending stairs
- A visible knee deformity
- A shorter walking distance than your job requires
- Inability to squat, rise from a chair or stand without using your arms
- Repeated swelling, stiffness or instability that limits work
Knee replacement suitability by age depends on X-ray evidence of joint damage, disability, general health, rehabilitation capacity and work demands rather than chronological age alone. The decision about knee replacement for working adults should account for heart and lung health, diabetes control, frailty, home support and the physical demands of the job.
A younger adult should discuss revision because an implant placed in the 40s or 50s may need replacement during a longer lifetime of use. Advanced age alone does not rule out surgery if the person can safely undergo treatment and participate in rehabilitation.
Which treatment fits the knee and the job?
The best choice depends on both the damaged knee and the work it must perform. Arthritis confined to one compartment may suit partial knee replacement; arthritis across two or three compartments usually points toward total knee replacement.
Nonoperative care or temporary job modification remains sensible when pain is manageable or surgery would not restore safe function.
| Option | What it means | When it applies |
|---|---|---|
| Total knee replacement | Replaces the damaged joint surfaces | Arthritis affects multiple compartments, with persistent pain and loss of function |
| Partial knee replacement | Replaces one diseased compartment while preserving more of the knee | Disease is isolated, ligaments work well, deformity is limited, and movement remains good |
| Nonoperative treatment | Physiotherapy, strengthening, medicines, injections, weight management when appropriate, and activity changes | Symptoms remain manageable or imaging does not match severe functional loss |
| Temporary job modification | Reduces exposure while treatment continues or recovery develops | You need shorter shifts, seated breaks, lighter duties, or fewer stairs before deciding on surgery |
The surgeon matches pain location with examination and imaging. Ligament stability, deformity, stiffness, bone damage and the X-ray pattern matter; a scan alone does not select the operation. Knee replacement for standing jobs is less suitable if instability, severe stiffness or widespread weakness would still prevent safe work.
- Shift length and standing hours
- Walking distance, stairs or ladders, and uneven floors
- Kneeling, repeated squatting, lifting loads and rapid direction changes
- Safety footwear and access to seated breaks
For knee replacement for working adults and knee replacement for people who work on their feet, the surgeon, physiotherapist, occupational-health professional and employer should compare these demands with required strength, balance and mobility. A phased plan may solve the problem without immediate surgery.
What does knee replacement recovery mean for returning to work?
Knee replacement recovery work is measured by what your job demands, not by how well the incision looks. Many people resume ordinary daily activities within roughly 3 to 6 weeks, but knee replacement for people who work on their feet usually requires more time and planning than desk work.
- Early recovery focuses on wound care, prescribed exercises and a safe walking progression; physiotherapy then builds range of motion and quadriceps strength.
- Control swelling with rest, leg elevation, ice if advised, and activity increases that do not leave the knee significantly more swollen the next day.
- Arrange driving only after you can enter and exit safely, control the vehicle, and receive clearance from your surgeon; pain medicine and limited knee movement can make driving unsafe.
- Return through phased hours, seated breaks and lighter duties. Temporary limits on lifting, kneeling, ladders and rapid direction changes may be necessary.
- Wear supportive, stable footwear and continue strengthening after returning. Kneeling is often uncomfortable, so use padding and safe technique rather than forcing it.
Walking around your house or attending a short outpatient appointment does not prove that you can tolerate eight hours of repeated loading. Quadriceps weakness, fatigue and swelling can appear after several hours, even when short walks feel manageable.
A plan for knee replacement for standing jobs might begin with shorter shifts, scheduled sitting and leg elevation, then add hours as strength and swelling improve.
Knee replacement can restore useful mobility, but it does not create a normal knee, so your surgeon and rehabilitation team should set the progression rather than promise a fixed return date.
How does the job change the return-to-work plan?
Return timing depends on force, distance and workplace hazards, not just hours spent standing. Knee replacement for standing jobs may allow a teacher back sooner than a nurse because classroom walking differs from patient transfers and emergency movement.
| Role | Main demands | Return-to-work concern |
|---|---|---|
| Teacher | Classroom standing and walking | Build shift length and seated breaks |
| Nurse | Patient transfers and prolonged walking | Strength, balance and safe lifting |
| Retail worker | Shop-floor pacing and standing | Shorter shifts and lighter duties |
| Factory employee | Machine-area walking and safety rules | No safety-critical tasks while weak |
| Security guard | Patrol distances and rapid response | Walking endurance and stable balance |
| Delivery worker | Driving, vehicle loading and carrying | Loading limits and repeated stairs |
| Construction worker | Ladders, uneven ground, kneeling and lifting | Delay until control and strength return |
| Athlete | Running, jumping and contact | Low-impact training before impact sport |
For knee replacement recovery work, a phased return can start with shorter shifts, scheduled sitting, leg elevation and lighter duties. A knee replacement for working adults requires progression from controlled walking to repeated loading across a full shift; a person who manages a short appointment may still fatigue or swell at work.
Safety-critical duties wait until strength, balance and swelling are controlled.
Kneeling after replacement is often uncomfortable, not automatically harmful. Use padding and a safe technique; report persistent pain, instability, marked swelling or inability to kneel instead of forcing through it.
Walking, cycling and swimming are lower-impact choices. Repeated running, jumping and contact sports place different loads on the implant and usually require greater caution. That distinction matters in knee replacement for standing jobs and knee replacement for working adults.
What should you settle with the surgeon before choosing surgery?
Reliable mobility at work requires a decision about risks, restrictions and job demands, not just an operation date.
Knee replacement suitability by age depends on joint damage, disability, general health and rehabilitation capacity; someone in their 40s or 50s should discuss implant longevity and the higher lifetime possibility of revision because they may outlive the implant. Advanced age alone does not rule out surgery.
| Decision point | Settle with the surgeon | Why it matters at work |
|---|---|---|
| Implant longevity | Expected durability and revision possibility | Repeated loading may matter over a longer working life |
| Medical risk | Infection, fracture, loosening, medical illness and diabetes control | A complication can delay or prevent reliable mobility |
| Rehabilitation | Exercises, physiotherapy participation and measurable strength goals | Weakness or poor balance makes lifting and safety-critical tasks unsafe |
| Job demands | Walking distance, stairs, kneeling, lifting and uneven surfaces | A healed wound does not prove you can complete a full shift |
Take these questions to your consultation:
- What tasks must return, and what strength and walking distance are required?
- When can driving, stairs, lifting and kneeling resume?
- Can my employer provide modified duties, seated breaks or a phased return?
- Which restrictions apply to ladders, rapid direction changes and safety-critical work?
A knee replacement recovery work plan can be discussed with Dr.A.K.Sharma-Ortho & joint replacement surgeon in Noida, including imaging, medical risk, alternatives and job-specific restrictions.
After surgery, seek prompt medical assessment for fever, increasing redness or drainage, calf swelling or pain, sudden breathlessness, or new inability to bear weight.
Related service
Restore Mobility and Live an Active Life: Knee Replacement Surgery in Noida At Global Orthopaedics and Speciality Clinics in Noida, we understand... View service → |
Frequently asked questions
When should a working adult consider knee replacement?
Consider knee replacement when knee pain and loss of function continue despite a structured plan involving physiotherapy, strengthening, weight management when appropriate, medicines, injections and activity modification. The decision depends on symptoms, examination findings, imaging and daily limitations—not age alone.
Which treatment fits a knee and a standing job?
Treatment depends on the extent and location of joint damage, symptoms, physical demands and previous treatment. Options can include physiotherapy, medicines, injections, activity changes, osteotomy or knee replacement. A standing job makes symptom control and realistic workplace changes important parts of the decision.
What does knee replacement recovery mean for returning to work?
Recovery includes wound care, pain control, progressive exercises, walking rehabilitation and rebuilding strength. Return-to-work timing depends on healing, mobility, stamina and job demands. Desk work usually requires fewer physical demands than prolonged standing, walking, lifting or kneeling.
How does the job change the return-to-work plan?
A standing or physically demanding role may require a phased return, scheduled sitting breaks, reduced walking, limits on lifting and temporary avoidance of kneeling or squatting. Discuss the actual tasks, shift length and available adjustments with your surgeon and employer.
What should you settle with the surgeon before choosing surgery?
Ask how knee replacement fits your diagnosis, expected functional goals, rehabilitation schedule, driving and work restrictions, warning signs, and the tasks you need to resume. Share your job description so the recovery plan addresses standing, walking, lifting, stairs, kneeling and shift duration.
Keywords